

On September 30, 2026, the Centers for Medicare & Medicaid Services (CMS) finalized a rule to implement a mandatory Most Favored Nation (MFN)-based drug pricing model in Medicare Part B: the Global Benchmark for Efficient Drug Pricing (GLOBE) Model (Final Rule). Beginning January 1, 2027, the model will test alternative methods for calculating manufacturer rebates under the Medicare Part B inflation rebate program by tying applicable pricing benchmarks for model drugs to international pricing information, among other changes. The Final Rule for the GLOBE Model was published in the Federal Register on October 2, 2026, and the new regulations are codified at 42 C.F.R. Part 513 effective November 30, 2026.
CMS finalized most aspects of the GLOBE Model as proposed but announced several modifications. Consistent with the GLOBE Model proposed rule (Proposed Rule), the final GLOBE Model will apply to a defined set of Part B rebatable single source drugs and sole source biological products that meet specified eligibility criteria, including falling into certain therapeutic categories and meeting a spending threshold, and only to units furnished to beneficiaries in randomly selected geographic areas comprising approximately 25% of Original Medicare Part B beneficiaries. In response to comments, CMS will exclude orphan-only drugs, plasma-derived products, and certain cell and gene therapies from the GLOBE Model.
Participation remains mandatory for manufacturers of GLOBE Model drugs, which will owe an incremental rebate when the international benchmark-based rebate exceeds the Part B inflation rebate otherwise owed. However, CMS confirmed in the preamble to the Final Rule that manufacturers participating in the voluntary GENErating cost Reductions fOr U.S. Medicaid (GENEROUS) Model are exempt from GLOBE. CMS continues to rely on its authority under Section 1115A of the Social Security Act (SSA), which authorizes the Center for Medicare and Medicaid Innovation (CMMI) to test the GLOBE Model and waive statutory Medicare requirements as necessary.
CMS is delaying the GLOBE Model start date from the originally-proposed October 1, 2026, to January 1, 2027, and further delaying the performance period start date from October 1, 2026, to April 1, 2027.
Key changes between the Final Rule and CMS’s original proposals are discussed below.
CMS has not yet finalized the companion Medicare Part D Guarding U.S. Medicare Against Rising Drug Costs (GUARD) Model. The GUARD Model was proposed alongside GLOBE in December 2025 with a contemplated start date of January 1, 2027.
The Federal Register notice for the Final Rule is available here, CMS's press release here, and the model webpage here.
Our alert on the GLOBE and GUARD proposed rules is available here.
Overview
The GLOBE Model will commence January 1, 2027, with an option for voluntary manufacturer data reporting, followed by a five-year performance period running from April 1, 2027, through March 31, 2032, with rebate invoicing, payment, and reconciliation continuing through March 2034, for a seven-year model period overall. CMS will evaluate the model’s impact in accordance with the CMMI statutory evaluation framework, including by assessing changes in Medicare spending for beneficiaries residing in model geographic areas, as well as effects on quality of care, access to drugs, and utilization patterns.
Which manufacturers are required to participate in the GLOBE Model?
- Proposed Rule: Model participation would be mandatory for all manufacturers of Part B rebatable drugs that are designated as GLOBE Model drugs, with GLOBE Model rebates due when furnished to a GLOBE Model beneficiary.
- CMS clarified that a model drug may have multiple manufacturers reporting average sales price (ASP) to CMS, including when there is a manufacturer involved in the repackaging or relabeling or when more than one manufacturer markets the drug within the U.S. In those cases, all manufacturers of the model drug would be required to participate.
- Consistent with the definition for the Part B inflation rebate program, CMS proposed to define “manufacturer” by cross reference to the definition in the Medicaid Drug Rebate Program (MDRP) statute (42 U.S.C. § 1396r-8(k)(5)), which identifies the manufacturer of a drug by its National Drug Code (NDC).
- CMS also stated the following regarding manufacturers that are involved in other CMMI models: “If certain manufacturers were excluded [from the GLOBE Model] due to interactions with other CMS Innovation Center models or for any other reason, the impacts from this proposed demonstration could be significantly less than described in this analysis.”
- Final Rule: CMS finalized the mandatory participation policy as proposed, as reflected in the definition of “GLOBE Model participant,” which includes no exceptions. However, CMS simultaneously confirmed in preamble guidance that it intends to use its authority under SSA § 1115A(d)(1) to waive participation for otherwise eligible manufacturers that participate in the voluntary GENEROUS Model under Medicaid during the same calendar quarter, “as necessary for purposes of the GENEROUS Model test.” While rolling out the GENEROUS Model, CMS “determined that a manufacturer’s participation in the GLOBE Model could impact CMS’s ability to isolate the effects of the GENEROUS Model.” Exempting GENEROUS Model participants reduces CMS’s estimated number of manufacturers of GLOBE Model eligible drugs from 19 to 4, based on the manufacturers with signed GENEROUS agreements in place as of August 17, 2026. For all other CMMI models, CMS will monitor for any potential issues related to model overlap and will propose operational adjustments to the GLOBE Model as necessary.
Which drugs are covered by the GLOBE Model?
-
Proposed Rule: Eligible model drugs would be drugs and biologicals that satisfy all of the following criteria:
- Must qualify as a “Part B rebatable drug”: Under existing regulations, such term is defined to mean single source drugs or biological products for which payment is made under Part B, including biosimilar biological products but excluding the following (which thus are also not model drugs):
- Qualifying biosimilar biological products, defined to mean biosimilars that have an ASP not more than that of the reference biological product during a particular calendar quarter during a five-year period beginning October 1, 2022, or, for a biosimilar approved after October 1, 2022, and before December 31, 2027, the five-year period beginning with the first quarter in which a payment was made for the product.
- Products with historically excepted grouped Healthcare Common Procedure Coding System (HCPCS) codes (e.g., within the same billing and payment code as of October 1, 2003, and which are treated as multiple source drugs).
- Products billed under a not otherwise classified (NOC) code.
- Radiopharmaceutical drugs and biological products.
- Skin substitutes.
- Certain vaccines and monoclonal antibodies.
- Generic drugs (approved under Abbreviated New Drug Applications (ANDAs)).
- Drugs and biological products with average total allowed charges below the applicable threshold.
-
Must fall within at least one of the following USP therapeutic categories: Antigout agents, antineoplastics, blood products and modifiers, central nervous system agents, immunological agents, metabolic bone disease agents, or ophthalmic agents as specified in the United States Pharmacopeia Drug Classification (USP DC) published for 2025.
-
Must qualify as a single source drug or sole source biological product:
- A “single source drug” would have the same meaning as defined in the ASP statute, 42 U.S.C. §1395w–3a(c)(6)(D), which means a drug that is not a multiple source drug (i.e., a drug that does not share a HCPCS code with another drug, among other requirements) and which is produced or distributed under a New Drug Application (NDA) approved by the Food and Drug Administration (FDA), including a drug product marketed by any cross-licensed producers or distributors operating under the NDA.
- CMS proposed to define a “sole source biological product” as a biological product licensed by the FDA under a Biologics License Application (BLA) and that, at time of evaluating for inclusion into the model for each applicable ASP calendar quarter, is not the reference biological product for a biosimilar licensed by the FDA in a BLA. The biosimilar must be recognized in the FDA’s Purple Book and identified as sold or marketed in FDA’s NDC Directory. CMS stated in the preamble language that biosimilar biological products would be excluded from the GLOBE Model. However, that exclusion was not expressly incorporated in the proposed regulatory language.
-
Must satisfy the spending threshold: Drugs must be included in a HCPCS Level II code with Medicare Part B FFS spending greater than $100 million over a 12-month period ending 6 months prior to the start of the applicable calendar quarter.
- A model drug would continue to be included in the proposed GLOBE Model once it meets this criterion for one applicable calendar quarter, even if Medicare Part B FFS spending falls below $100 million over a later 12-month period.
-
Must not be in one or more of the below-described categories (which are exempted from the GLOBE Model):
- A Part B rebatable drug for which CMS has not yet established a specified amount for the first applicable calendar quarter. “This proposal would ensure that the GLOBE Model and the Medicare Part B Drug Inflation Rebate Program would treat a subsequently approved drug (that is, a drug first approved or licensed by the FDA after December 1, 2020) in a similar manner. In other words, until a specified amount is established by CMS for a subsequently approved Part B rebatable drug, that drug would not be considered for the GLOBE Model.”
- A Part B rebatable drug for which a maximum fair price (MFP) under the Medicare Drug Price Negotiation Program (DPNP) is in effect.
- A drug or biological product that is no longer a Part B rebatable drug is removed for the applicable calendar quarter in which it is no longer a Part B rebatable drug.
Once a drug or biological product has been identified as a model drug, it would remain in the GLOBE Model unless the drug or biological product becomes multiple-source (i.e., is no longer a single source drug or sole source biological product) or meets the exclusions noted above. CMS proposed to maintain a GLOBE Model Drug List that will be published on the model webpage and updated quarterly.
- Final Rule: CMS finalized the drug inclusion criteria as proposed, with minor terminology updates, but will exclude orphan-only drugs, plasma-derived products, and certain cell and gene therapies. Specifically, the GLOBE Model will exclude Part B rebatable drugs that are (i) “designated as a drug for one or more rare diseases or conditions . . . and for which the only approved indication (or indications) is for one or more such rare diseases or conditions” (emphasis added), (ii) “products listed on the FDA’s Approved Cellular and Gene Therapy products website,” and (iii) plasma-derived products as defined in 42 C.F.R. § 427.400. In addition, CMS confirmed that separately payable radiopharmaceuticals and other products “not paid under section 1847A . . . fall within an excluded product category for purposes of the Part B rebatable drug definition” and, as such, “would not be in the GLOBE Model.” CMS declined requests from commenters to also exclude oncology medicines, products receiving FDA Breakthrough Therapy, Fast Track, or Priority Review designations, and Part B drugs and biologicals that share the same or overlapping FDA-approved indications with an excluded biosimilar or generic product.
CMS added a table to the regulations to clarify the applicable quarters for determining whether the spending threshold is met. CMS further modified the regulations to specify that the minimum spend threshold will be adjusted for inflation each applicable calendar quarter when CMS evaluates Part B rebatable drugs not previously included in the Model. CMS will adjust the threshold “by the percentage increase in the CPI-U for the consecutive 12-month period ending 6 months prior to the start of such applicable calendar quarter,” or, if unavailable, the most recent 12-month period prior to the specified 12-month period for which data are available.
Which beneficiaries are eligible?
- Proposed Rule: CMS would enroll a select cohort of Medicare Part B beneficiaries, identified based on coverage and geographic criteria, which would comprise approximately 25% of the Medicare FFS population. To qualify, a beneficiary must be enrolled in Medicare Part B, have Medicare Part B FFS as his/her primary payer, and have an address of record within the GLOBE Model geographic areas selected for inclusion by CMS. The geographic areas would be identified by ZIP code, and CMS would provide a table on the GLOBE Model website no later than 30 days before the start of the model that identifies the applicable ZIP codes. CMS would also add eligible beneficiaries to a GLOBE Model Eligible Beneficiary List and update the Medicare claims processing systems to reflect beneficiary eligibility. Once identified by CMS as a model eligible beneficiary, the beneficiary would remain in the model unless the beneficiary becomes ineligible (e.g., by no longer having Medicare Part B FFS as the primary payer). A beneficiary would remain included in the model even if the beneficiary moves to an address that is no longer in the model’s identified geographic areas.
- Final Rule: CMS finalized the beneficiary eligibility criteria as proposed, with minor adjustments to the timing for identifying and publishing the eligible beneficiaries and applicable geographic areas. CMS will randomly select the geographic areas no later than 90 calendar days before the model performance period starts, on April 1, 2027, instead of 60 calendar days as proposed. The agency will identify the applicable geographic areas on the GLOBE Model website no later than 75 calendar days, instead of 30 days, before the model performance period begins. Further, instead of 30 days before the model starts on January 1, 2027, CMS will identify the initial beneficiaries eligible for the GLOBE Model approximately 30 days prior to the start of the model performance period on April 1, 2027. CMS will update the GLOBE Model Eligible Beneficiary List no more frequently than monthly.
How is the GLOBE Model rebate calculated?
- Proposed Rule: Manufacturers would owe an incremental GLOBE Model Rebate amount when the rebate calculated using the model’s MFN-based rebate formula exceeds that under the existing statutory inflation rebate calculation. The details of this calculation are as follows:
- Incremental per unit GLOBE Model rebate amount. CMS proposed to calculate the incremental per unit GLOBE Model rebate amount by subtracting the per unit Part B inflation rebate amount from a per unit GLOBE Model rebate amount.
Incremental per unit GLOBE Model rebate amount = [(the specified amount for purposes of the Part B inflation rebate program (generally 106 percent of the lesser of the ASP or Wholesale Acquisition Cost (WAC) for an applicable quarter or rebate quarter) – per unit GLOBE Model benchmark amount) – (the same specified amount – per unit Part B inflation-adjusted payment amount)]
For example, if the specified amount is $106, the GLOBE Model benchmark amount is $70, and the inflation-adjusted payment amount is $80, the difference between the two rebate amounts (the Global Model rebate amount) would be $10 ($36 ($106-$70) - $26 ($106-$80)).
If the per unit GLOBE Model rebate amount calculates as less than $0, then CMS would set the per unit GLOBE Model rebate amount as $0.
- Incremental per unit GLOBE Model rebate amount. CMS proposed to calculate the incremental per unit GLOBE Model rebate amount by subtracting the per unit Part B inflation rebate amount from a per unit GLOBE Model rebate amount.
- GLOBE Model billing units. CMS proposed to identify the GLOBE Model billing units as the billing units for an applicable quarter for purposes of the Part B inflation rebate calculation “where, on the date of service, the Medicare beneficiary was identified by CMS as a GLOBE Model eligible beneficiary and for which Medicare Part B FFS made separate payment.”
- Apportionment. Where the NDCs of more than one manufacturer are assigned to a particular billing and payment code for a GLOBE Model drug, CMS proposed to use the same methodology to apportion the rebate across manufacturers as used for Part B inflation rebates (i.e., by volume of billing units reported as sold for an NDC assigned to that billing and payment code).
- Adjustments for shortage and for severe supply chain disruption. For GLOBE Model drugs in shortage and for “GLOBE Model biosimilar biological products when there is a severe supply chain disruption,” the incremental GLOBE Model rebate amount would be reduced proportionally to the rebate reduction under the standard Part B inflation rebate program (assuming such products are included in the final GLOBE Model). Further, although CMS does not state so explicitly, to the extent that there are GLOBE Model drugs that are plasma-derived products, the shortage adjustment should also include an increased reduction, consistent with the reduction for such products under the Part B inflation rebate program. These adjustments may be time limited, again consistent with the Part B inflation rebate program.
- Final Rule: No significant changes. However, because CMS has affirmatively excluded biosimilar biological products from the GLOBE Model, CMS has removed language related to the GLOBE Model rebate calculation that would have allowed for a reduction in the rebate in the case of a shortage or severe supply chain disruption. CMS also noted in response to comments that 340B units should be excluded from the GLOBE Model billing units because they are excluded from the Medicare Part B inflation rebate units.
What are the benchmarks and how are they identified?
- Benchmark framework.
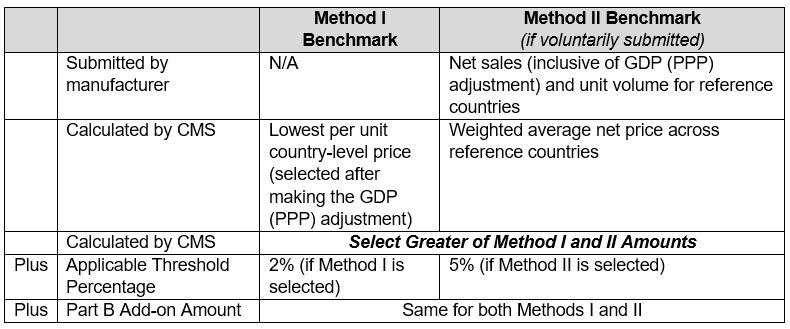
- Proposed Rule: The per unit GLOBE Model benchmark would be the greater of (1) a Method I GLOBE Model benchmark identified and calculated by CMS or (2) a Method II GLOBE Model benchmark calculated based on data reported voluntarily by manufacturers. The ultimate formula used is as follows and is described further below:
- Final Rule: Adopted without substantive change.
- Method I GLOBE Model benchmark.
- Proposed Rule: Under Method I, “CMS [proposed to] calculate[] the per unit country-level price for the international drug by country for each country . . . for which international drug pricing information is available” for the countries included in the GLOBE Model (noted below) and select the lowest per unit country-level price to use as the Method I GLOBE Model benchmark, subject to the adjustments noted below. The identification and calculation of the Method I GLOBE Model benchmark would be made as follows:
- Data and identification of international analogs. CMS would rely on data sources identified according to whether they rely on certain standardized criteria, including that data identify relevant international analogs to the GLOBE Model drug by reference to dosage form and route of administration, strength, concentration, and units and that the data contains pricing, volume, or sales data.
- The data would be “made available by private companies . . .” as opposed to public data sources. Examples cited by CMS include IQVIA’s MIDAS and the Global Data Pharmaceutical Prices (POLI) dataset.
- CMS would prioritize data sources with data from the most reference countries in the model and, if available, that incorporate discounts, rebates, or other price concessions.
- CMS would exclude “pricing information at the dosage form and strength level for a country that falls below 5 percent of the average price in the U.S.”
- In contrast to the GUARD Model, where CMS suggested it may use misaligned product data to identify international analogs in certain cases, as noted below, CMS did not expressly address how it will identify the Method I GLOBE Model benchmark where there are no international analogs that align with GLOBE Model drugs based on the above criteria. Instead, CMS focused on the process for identifying appropriate international data sources, suggesting it believes it can find a data source with an appropriate international analog.
- Benchmark price quarter. The Method I benchmark would be calculated for a single fixed quarter for each GLOBE Model drug that is “two calendar quarters prior to the first applicable calendar quarter to which the total GLOBE Model rebate amount would apply,” meaning:
- The benchmark quarter for Method I would be identified “for the first applicable calendar quarter for which the drug is a GLOBE Model drug and this benchmark [would] remain[] in place for each applicable calendar quarter thereafter until the end of the model performance period.”
- This would align with the two-quarter lag for purposes of calculating ASP-based payment limits.
- However, this single fixed quarter would not necessarily align with the Part B inflation rebate benchmark quarter, which is defined by statute, in general, as 3Q 2021 for drugs that are first approved or licensed on or before December 1, 2020, and the third full calendar quarter after the drug is first marketed for drugs approved or licensed after December 1, 2020.
- Data and identification of international analogs. CMS would rely on data sources identified according to whether they rely on certain standardized criteria, including that data identify relevant international analogs to the GLOBE Model drug by reference to dosage form and route of administration, strength, concentration, and units and that the data contains pricing, volume, or sales data.
- Final Rule: CMS finalized the core Method I benchmark framework, with modifications to the data source identification and selection processes.
- Where international pricing information is unavailable when a drug first qualifies for the Model, CMS will “apply the process for identification of the per unit Method I GLOBE Model benchmark for subsequent applicable calendar quarters during the model performance period until a per unit Method I GLOBE Model benchmark is identified.”
- CMS also finalized that its identification of the Method I GLOBE Model benchmark amount would reflect “updates to the international drug pricing information for international analogs for a GLOBE Model drug” made by the organization that maintains the selected data source “within 90 days from the end of the calendar quarter for which drug pricing information is compiled,” i.e., the first applicable calendar quarter for which the drug is a GLOBE Model drug or for which CMS can identify a Method I GLOBE Model benchmark for the drug. Data updates made more than 90 days from the end of the applicable calendar quarter would not be used to identify the Method I GLOBE Model benchmark amount, which remains in place until the end of the model performance period.
- CMS made several modifications to the hierarchy used to select the data source for each Model drug. Among other changes, CMS addressed “commenters’ concerns about the potential use of international drug pricing information from prior periods,” by prioritizing data sources with data for the applicable quarter, while maintaining the potential to look to earlier periods as “a reasonable safeguard against the potential effect of manufacturers limiting the availability of international drug pricing information in existing data sources.”
- CMS disagreed with commenters that “it would be costly and burdensome for manufacturers to obtain and use existing data sources,” which “would be necessary to judge how CMS determined the Method I benchmark.” CMS responded that the existing data sources “are widely used by interested parties within the biopharmaceutical industry” and, “[a]s such, it may be likely manufacturers of GLOBE Model drugs have access to and familiarity with these existing data sources, and that any financial burden associated with access to such data source related to participation in the GLOBE Model would be minimal.”
- Proposed Rule: Under Method I, “CMS [proposed to] calculate[] the per unit country-level price for the international drug by country for each country . . . for which international drug pricing information is available” for the countries included in the GLOBE Model (noted below) and select the lowest per unit country-level price to use as the Method I GLOBE Model benchmark, subject to the adjustments noted below. The identification and calculation of the Method I GLOBE Model benchmark would be made as follows:
- Method II GLOBE Model benchmark.
- Proposed Rule: Under Method II, CMS would rely on international drug net pricing data submitted voluntarily by manufacturers for an applicable ASP calendar quarter (i.e., the quarter that is two quarters before the applicable quarter for which a rebate might be due) to calculate a volume-weighted average net price at the HCPCS Level II code billing unit level across reference countries represented. If a manufacturer does not submit international drug net pricing data, then the Method I GLOBE Model benchmark would be the GLOBE Model benchmark for the applicable calendar quarter. Information reported by manufacturers for the Method II GLOBE Model benchmark would be subject to the following requirements for each performance year:
- Submission requirements. Each submission would be required to include certain basic data elements. Manufacturers would be expected to submit net pricing data through one of two approaches (i.e., the “streamlined” or “limited” options) that differ in “the level of aggregation allowed for the submission of gross sales, net sales, and sales volume that was used by the manufacturer to calculate the across country volume-weighted average Gross Domestic Product (GDP) purchasing power parity (PPP)-adjusted net pricing per HCPCS billing unit.” Both contain the same categories of data, and both would include adjustments for GDP (PPP). Manufacturers would select one submission option for all applicable international analogs to a GLOBE Model drug. Manufacturers could choose whether to make these submissions for all or only a subset of their GLOBE Model drugs.
- Benchmark price quarter. Unlike the Model I benchmark price quarter, the Model II benchmark price quarter would not be fixed but rather would float and equal the applicable ASP calendar quarter, i.e., the quarter that is two quarters before the applicable calendar quarter for which a rebate would be due.
- Data submission timing. Each submission would be due no later than 30 days after the end of the applicable ASP calendar quarter.
- Corrections and restatements. CMS proposed to allow corrections and restatements of data within 30 calendar days of the submission deadline or 5 business days of a request by CMS.
- CMS verification. CMS would “conduct a verification review to determine whether the submission meets the submission requirements.”
- Confidentiality. CMS proposed to “maintain[] the confidentiality of information submitted . . . to the extent permitted by law and in accordance with applicable privacy and security requirements.” Further, CMS proposed that it would not disclose manufacturer-submitted international drug net pricing information in a form which discloses the identity of a specific manufacturer except as CMS deems necessary to carry out the GLOBE Model calculations.
- Data agreement. A manufacturer that elected to submit international pricing information for a GLOBE Model drug must enter into a data agreement effective prior to the first submission. The agreement would remain in effect for the duration of the GLOBE Model unless terminated by either the manufacturer or CMS. CMS has not yet released the data agreement.
- Final Rule: CMS finalized the core Method II benchmark framework but addressed cases where manufacturers may lack access to international pricing information. CMS finalized “an option as part of the voluntary manufacturer submission framework that would allow manufacturers to pursue the voluntary submission of international drug net pricing data even when they are unable to obtain all required data elements for every international analog.” Such manufacturers instead “would submit an explanation as part of the reasonable assumptions, which would be subject to CMS review.”
- Proposed Rule: Under Method II, CMS would rely on international drug net pricing data submitted voluntarily by manufacturers for an applicable ASP calendar quarter (i.e., the quarter that is two quarters before the applicable quarter for which a rebate might be due) to calculate a volume-weighted average net price at the HCPCS Level II code billing unit level across reference countries represented. If a manufacturer does not submit international drug net pricing data, then the Method I GLOBE Model benchmark would be the GLOBE Model benchmark for the applicable calendar quarter. Information reported by manufacturers for the Method II GLOBE Model benchmark would be subject to the following requirements for each performance year:
- Reference countries.
- Proposed Rule: CMS proposed criteria for identifying the set of reference countries for purposes of determining the two GLOBE Model benchmarks as “non-U.S. Organization for Economic Co-operation and Development members . . . as of October 1, 2025 with: (1) a real GDP per capita that is at least 60 percent of the U.S. real GDP per capita, as estimated and available in the Central Intelligence Agency (CIA) World Factbook; and (2) an annual real GDP that is at least $400 billion (as measured in U.S. dollars) as estimated and available in the CIA World Factbook, as determined by CMS.” If the criteria are finalized as proposed, the following set of 19 reference countries would be used: Australia, Austria, Belgium, Canada, Czechia, Denmark, France, Germany, Ireland, Israel, Italy, Japan, Netherlands, Norway, South Korea, Spain, Sweden, Switzerland, and the United Kingdom.
- Final Rule: Adopted without substantive change.
- GDP (PPP) adjustment.
- Proposed Rule: Data used to calculate both GLOBE Model benchmarks would be adjusted for purchasing power parity (PPP) using GDP data available in the CIA World Factbook. To calculate the GDP (PPP) adjuster, CMS would “divide the U.S. real GDP per capita by the [relevant] country’s real GDP per capita and round the result to the third decimal place.” CMS would “publish a supplemental document on the GLOBE Model website with details on which GDP (PPP) adjuster would be used for each applicable ASP calendar quarter.” For the Method I GLOBE Model benchmark, the GDP (PPP) adjustment is made to each reference country’s pricing information before selecting the lowest amount as the Method I GLOBE Model benchmark. For the Method II GLOBE Model benchmark, manufacturers would make the GDP (PPP) adjustment as part of their submissions.
- Final Rule: Adopted with modification to the data source. CMS will use the World Bank and the International Monetary Fund for GDP and PPP data in light of the CIA’s announcement to cease publishing the World Factbook.
- Benchmark adjustments.
- Proposed Rule: CMS would make additional adjustments to the GLOBE Model benchmarks by applying:
- An “applicable threshold percentage” increase, which is “a modest increase to account for potential differences between the U.S. market and markets in the reference countries that may remain after allowing for economic and purchasing power differences.” For the Method I GLOBE Model benchmark, CMS proposed an “applicable threshold increase” of “a de minimus amount of up to 2 percent,” given that this benchmark “does not likely reflect the full range of confidential discounts and net pricing” and “because drug pricing information that is made available to existing data sources becomes accessible to drug purchasers, the variation among such prices for a given drug would be expected to lessen over time.” For the Method II benchmark, CMS proposed to use a higher applicable threshold percentage of 5 percent, “[t]o account for the likelihood of larger price variations across countries that may occur in actual transaction prices abroad.”
- An “add-on percentage amount,” which would equal the dollar value of the add-on percentage included in the Medicare Part B drug payment limit for the GLOBE Model drug for the applicable calendar quarter. This amount would generally be 6 percent for drugs reimbursed based on ASP.
- Final Rule: Adopted without substantive change.
- Proposed Rule: CMS would make additional adjustments to the GLOBE Model benchmarks by applying:
How is beneficiary coinsurance calculated?
- Proposed Rule: Under the Part B inflation rebate program, CMS calculates a reduced beneficiary coinsurance amount where the specified amount (i.e., 106 percent of the lesser of ASP or WAC for an applicable quarter) exceeds the inflation-adjusted payment amount. In that case, coinsurance is calculated as 20 percent of the inflation-adjusted payment amount instead of 20 percent of the payment limit for the quarter. The GLOBE Model would test an alternative calculation for beneficiary coinsurance. Where the payment limit exceeds the per unit GLOBE Model benchmark amount for a GLOBE Model drug, coinsurance would be calculated as 20 percent of the per unit GLOBE Model benchmark amount instead, applied as a percentage of the payment amount. To ensure that beneficiaries would pay no more than they would absent the model, CMS stated that it would compare the benchmark amount to the inflation-adjusted payment amount and use the lesser of the two in computing the coinsurance. When the GLOBE Model reduced beneficiary coinsurance would apply, “the provider or supplier would reduce the amount of coinsurance charged to the beneficiary and the portion of the Medicare Part B allowed amount that would be payable by Medicare Part B would be adjusted upwards.”
- Final Rule: Adopted with clarifying changes. CMS clarified in the finalized regulatory text that the coinsurance adjustment is determined solely by CMS and administrative and judicial review is precluded, consistent with the Part B inflation rebate statute and Section 1115A of the SSA. In addition, CMS clarified that claims not eligible for inflation-adjusted coinsurance are not subject to the GLOBE Model adjustment. CMS will include each model drug’s coinsurance percentage in the quarterly GLOBE Model drug list that it will publish.
What is the rebate invoicing/suggestion of error process?
- Proposed Rule: CMS proposed two alternative approaches for invoicing manufacturers for GLOBE Model rebates: a “combined” model and an “incremental” model. Both approaches would rely on the same underlying GLOBE Model rebate calculation and the same per unit GLOBE Model rebate amount. What differs between the two approaches is how and when CMS would invoice manufacturers and administer the Suggestion of Error and reconciliation processes noted below. CMS intended to adopt one of the below approaches, or a “similar approach” after considering comments.
- Combined Model: Under this approach, CMS would delay Medicare Part B inflation rebate program Preliminary Rebate Reports by up to two months and provide manufacturers with a single, combined report for both the Medicare Part B inflation rebate program and the GLOBE Model. The process for the rebate report under the combined approach would align with the Medicare Part B inflation rebate program with minor modifications. While CMS proposed to issue the Preliminary Rebate Reports two months later, the regular cadence for rebate reports and reconciliations would remain unchanged. Manufacturers would use the existing Part B Suggestion of Error process to raise concerns about mathematical errors in preliminary rebate calculations.
- Incremental Model: Under this approach, CMS would invoice the GLOBE Model rebate amounts to manufacturers using a process that would be separate from, but harmonized with, the Medicare Part B inflation rebate program.
- CMS would issue the GLOBE Model Preliminary Rebate Report at least one month before issuing the GLOBE Model Rebate Report.
- Manufacturers would be required to submit a Suggestion of Error within 10 calendar days of receiving the Preliminary Rebate Report.
- CMS would issue the GLOBE Model Rebate Report no later than eight months after the end of each applicable calendar quarter.
- CMS would also adopt a reconciliation approach similar to that under the Medicare Part B inflation rebate program.
- Final Rule: CMS finalized the “incremental” invoicing approach rather than the “combined” approach and finalized all other aspects of the rebate invoicing/suggestion of error process as proposed. CMS was “persuaded by commenters’ concerns that the combined approach would impose administrative burdens on manufacturers that have no GLOBE Model obligations,” in contrast to the “incremental” approach, which “allows GLOBE Model-specific rebate calculations and reporting to proceed while preserving the Medicare Part B Drug Inflation Rebate Program’s timelines and minimizing operational disruption to the broader manufacturer community.” CMS revised the definition of “date of receipt,” to align with the “incremental” approach, so as to refer to the calendar day after CMS makes a GLOBE Model rebate amount report available to the manufacturer, instead of using the definition from the Part B inflation rebate regulations.
Are there appeals rights?
- Proposed Rule: Manufacturers would have no appeal rights with respect to CMS’s selection of model drugs, beneficiaries, or geographic areas, the total GLOBE Model rebate amount, or the calculation and application of the GLOBE Model beneficiary coinsurance percentage. CMS also proposed that the limitations on administrative or judicial review under the Part B inflation rebate program would apply to the GLOBE Model. Section 1115A(d)(2) of the SSA, the statute governing the authority of CMMI, also provides limitations on administrative and judicial review of aspects relating to CMMI models, including (but not limited to) the selection of models, organizations, sites, and participants involved in the models and the elements, parameters, scope, and duration of such models for testing.
Manufacturers would, however, have the right to appeal any civil monetary penalties (CMPs) imposed by CMS under the model, including determinations that the incremental GLOBE Model rebate amount due was not paid by the applicable payment deadline and CMS's calculation of that amount. Appeals would proceed under CMS’s existing CMP appeal procedures, including the right to a hearing following the exhaustion of administrative remedies.
- Final Rule: Adopted without substantive change. CMS declined to adopt “a more complex review process” as suggested by commenters.
Are there penalties?
- Proposed Rule: A manufacturer that fails to timely pay the incremental GLOBE Model rebate amount would be subject to a CMP equal to at least 125% of the incremental rebate amount due for the drug. A manufacturer that knowingly fails to comply with the GLOBE Model requirements, including the provisions in the data agreement, would also be subject to a CMP. A CMP would be in addition to any unpaid incremental rebate amount, and payment would be due within 60 days of the notice of imposition. Additionally, CMS proposed that if one or more grounds for enforcement action are met, it may take additional enforcement actions, including terminating the data agreement with the manufacturer, requiring the manufacturer to provide additional requested information to CMS or its designees, or subjecting the manufacturer to additional monitoring, auditing, or both. CMS would also have the authority to impose CMPs or terminate a manufacturer’s data agreement if the manufacturer submits false data or is subject to investigation or action by the U.S. Department of Health and Human Services (HHS) or the Department of Justice (DOJ) due to an allegation of fraud or significant misconduct.
- Final Rule: CMS finalized the penalty framework largely as proposed but revised the regulatory text to clarify that the CMP structure aligns with the CMP structure under the Medicare Part B Drug Inflation Rebate Program. CMS did not modify other aspects of the penalty framework, including the CMP appeal procedures and proposed policy for additional enforcement actions.
Are there statutory provisions that will be waived?
- Proposed Rule: For purposes of executing the above proposed GLOBE Model under Section 1115A of the SSA, CMS proposed to waive, to the extent necessary:
- The provisions of the Part B inflation rebate program calculation under Section 1847A(i)(3) of the SSA (42 U.S.C. §1395w–3a(i)(3)) and implementing regulations,
- The Part B inflation rebate program invoice timing requirements under Section 1847A(i)(1) of the SSA and implementing regulations, and
- Various provisions of Section 1833 of the SSA and implementing regulations related to beneficiary coinsurance and the Medicare portion of payment for a drug.
- Final Rule: Adopted without substantive change. CMS did not receive comments on these waivers.
What are the government price reporting obligations?
- Proposed Rule: In the preamble to the Proposed Rule, CMS specified that GLOBE Model rebates would be excluded from (i.e., not reduce) a manufacturer’s average manufacturer price (AMP), best price, and ASP calculations (and thus would not directly impact the 340B ceiling price). By statute, Part B inflation rebates made under Section 1847A(i) of the SSA are excluded from AMP and best price and sales exempt from best price are exempt from ASP. CMS stated that “the GLOBE Model rebate amounts are rebates under section 1847A(i) of the Act,” meaning that CMS interprets the exclusion that applies to those rebates to carry over to the GLOBE Model rebates. CMS acknowledged, however, that the Model could indirectly affect these price types if manufacturers lower their U.S. prices in response. CMS noted that “to the extent the proposed GLOBE Model may indirectly affect a drug's AMP and best price, the 340B prices would be affected.”
- Final Rule: No substantive changes.
Conclusion
We will continue to monitor for additional information related to the GLOBE Model as well as for other developments from CMS and the Administration related to MFN pricing policies. As always, it is important that you carefully review the model to identify all issues relevant to your organization. If you have any questions about what these developments may mean in practice, please contact any of the authors of this update or the Hogan Lovells Cadwalader lawyer with whom you regularly work.
The content of this article is intended to provide a general guide to the subject matter. Specialist advice should be sought about your specific circumstances.
[View Source]


